A large international study has revealed that fatty deposits within arteries are quite common even in adults who seem healthy and have never been diagnosed with heart disease.
The results imply that the processes leading to heart attacks and strokes can start many years before any symptoms show up.
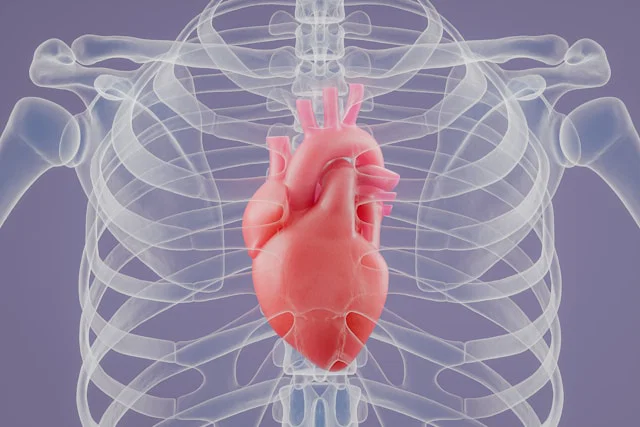
This condition, known as atherosclerosis, occurs when cholesterol, fat, calcium, and other substances accumulate in arterial walls, forming plaques.
As time passes, these plaques can enlarge and block arteries, restricting blood flow. They can also rupture, causing blood clots that may suddenly obstruct blood flow to the heart or brain, triggering a heart attack or stroke.
Cardiovascular disease remains one of the top causes of death worldwide. A challenge in preventing it is that atherosclerosis often develops silently for decades before symptoms like chest pain, fatigue, or breathing issues appear.
These findings come from the REACT project, a comprehensive international study aimed at mapping hidden artery build-up throughout adult life. Led by Professor Henning Bundgaard at Copenhagen’s Rigshospitalet and Dr. Borja Ibáñez from Spain’s CNIC, the research recruited 16,808 adults aged 18 to 70 in Denmark and Spain. None had prior diagnosed cardiovascular issues linked to atherosclerosis at the time of enrollment.
Participants underwent scans of crucial arteries: the carotid arteries in the neck, femoral arteries in the legs, and coronary arteries supplying the heart.
The findings were striking. Over half (57.1%) of participants had detectable plaque in at least one examined artery, despite having no previous diagnosis or symptoms.
Notably, signs of atherosclerosis appeared surprisingly early. About 1 in 13 individuals aged 18 to 29 already showed plaque presence in at least one artery.
The prevalence increased with age. Among those aged 60 to 70, roughly 90% had detectable plaque, highlighting how artery disease becomes more common as people grow older.
Patterns also emerged regarding where plaque tends to form. Most people with plaque in the coronary arteries also had signs in either the carotid or femoral arteries.
This is significant because examining neck and leg arteries with ultrasound is much easier than performing coronary artery scans. Ultrasounds are radiation-free, quick, portable, and increasingly accessible, making them a practical screening tool.
Typically, doctors estimate future cardiovascular risk through factors such as age, blood pressure, cholesterol levels, diabetes, and smoking habits. While risk calculators are helpful, they don’t directly reveal whether artery plaque has already developed.
The REACT team found that traditional risk scoring often misses many individuals who already have silent artery disease. This suggests that direct imaging of arteries might complement existing assessments, providing more detailed risk information.
Significant differences were observed between men and women. Men tended to develop atherosclerosis earlier, with their patterns appearing about 5 to 10 years sooner than women.
For women, most increases in plaque occurred between roughly ages 40 and 60—coinciding with menopause. Hormonal changes and shifts in cholesterol, blood pressure, and body composition during this period can influence cardiovascular health.
It’s important to note that finding plaque doesn’t guarantee a heart attack or stroke will happen. Many individuals with atherosclerosis never experience major cardiovascular events. Factors such as the amount, location, type, and progression of plaque all influence risk.
The first phase of the study, called REACT-DETECT, started in 2024. The project will continue with REACT-PROTECT from 2027 to 2032, aiming to determine whether prevention strategies based on artery imaging produce better health outcomes than current approaches.
This next step is key. Screening millions of healthy adults would require confirming that detecting silent plaques leads to interventions that genuinely improve health outcomes, justifying the costs, efforts, additional testing, and potential anxiety involved.
The study’s strength lies in its large sample size, broad age range, and direct assessment of arteries in multiple locations. Nonetheless, since participants were from Denmark and Spain, further research is needed to see how applicable these findings are to diverse populations with different genetics, diets, healthcare systems, and cardiovascular risks.
Collaborations are underway with researchers in India, Singapore, Tanzania, and Mexico to explore whether the pattern of silent atherosclerosis is consistent across various demographic and geographic backgrounds.
Results were presented at the ESC Congress 2026 and simultaneously published in the New England Journal of Medicine, offering a thorough insight into how atherosclerosis appears and progresses in adulthood.
Overall, the study challenges the notion that artery disease mainly affects the elderly. Its primary message is that the biological process underlying heart attacks and strokes can begin quite early in life.
While this emphasizes the need for improved prevention strategies, it doesn’t mean routine artery scans are recommended for everyone now. More evidence from future research is needed to determine whether screening can truly save lives.
Until then, managing well-established risk factors—like quitting smoking, controlling blood pressure, lowering LDL cholesterol, managing diabetes, staying active, and eating healthily—remains the cornerstone of cardiovascular prevention.
If you’re interested in health updates, consider exploring studies on low-dose lithium supplements, egg consumption, and their links to heart health. Also, look into recent research on potatoes and hypertension, as well as the best bread options for those with heart conditions.